The right surgeon is not determined by years in practice, online ratings, or the word “best.” You need to compare the surgeon’s experience with your exact operation, verify credentials and hospital resources, understand whether surgery is the right first treatment, and ask questions that reveal how the team will manage risks and unexpected findings.
Key takeaways
- Confirm surgery matches your cancer stage and treatment goal.
- Ask about experience with your exact operation and cancer type.
- Compare hospital outcomes, complication rates, and multidisciplinary support.
- Use the consultation to test whether the treatment plan is clear and complete.
Confirm That Surgery Is the Right First Step
Before agreeing to an operation, review the cancer stage and whether treatment aims to cure, control, or relieve symptoms. Ask the team to explain the biopsy results, have pathology slides reviewed by a specialist, and reconcile that report with CT scan imaging and the purposes of CT scans in cancer staging, MRI, and PET-CT imaging.
These findings can reveal local invasion, lymph nodes, distant metastases, or unresectable disease, but scans do not replace tissue diagnosis.
Ask these questions before choosing a surgeon:
- Could molecular testing or biomarker tests change treatment or the operation?
- Would neoadjuvant treatment—chemotherapy, immunotherapy, hormone therapy, or radiation—shrink the tumour or show treatment sensitivity before surgery?
- Can you obtain the actual pathology slides or tissue blocks, imaging files and reports, laboratory results, and operative recommendation for a second opinion?
- Will a multidisciplinary tumour board review the completed pathology and imaging?
- When will the final surgical pathology report be available, and how will it determine further treatment?
| Finding | What it may change | Question to ask |
|---|---|---|
| Localized, resectable tumour | Surgery may be the first step | What benefit justifies operating now? |
| Potentially downstageable tumour | Neoadjuvant treatment may reduce tumour size or operation extent | Would treatment first improve the result? |
| Unresectable disease or distant metastases | Systemic treatment may precede or replace surgery | Is surgery treating cancer, preventing a complication, or relieving symptoms? |
| Inherited-risk features | Genetic counseling may alter the extent of surgery | Could a limited operation leave substantial future cancer risk? |
Check Training, Credentials, and Experience With Your Exact Operation
A qualified surgeon should have current certification in the specialty that matches your cancer and documented experience with the exact operation—not merely many years in practice.
1. Match the specialty to the procedure. Cancer surgery may come through general surgery, colorectal surgery, thoracic surgery, gynecologic oncology, urology, or breast surgery. Ask which specialty board certification the surgeon holds and whether it is current.
2. Complete these specialist training fellowship verification steps: check the surgeon’s hospital profile, medical council register, training institution, fellowship dates, and professional-society listing. Medical council verification confirms an active licence and disciplinary history; it does not prove expertise in your operation. Where applicable, use the American Board of Medical Specialties directory to confirm board certification.
3. Ask for cancer-specific operative experience in writing. “I treat many cancer patients” is too broad. Ask how many operations matching your cancer, stage, and proposed procedure the surgeon performed during the past 12 months, and how many they personally performed rather than supervised.
4. Request procedure-specific surgical volume and comparable outcomes: major complications, reoperation, readmission, operative mortality where relevant, conversion from laparoscopic or robotic surgery to open surgery, and length of stay. Ask whether the figures cover the surgeon’s own cases and the same operation.
5. Confirm hospital privileges for the proposed operation. Ask whether the hospital has intensive care, interventional radiology, pathology, reconstruction, and emergency coverage suited to your risks. Hospital privileges are a minimum safety check, not proof that the surgeon is the best choice.
Ask for independent evidence such as published research, audited patient-care records, and review of your case at a multidisciplinary tumour board. Do not treat a “best surgeon” label or a fellowship alone as evidence of current competence.
Compare Surgeons Using Hospital and Outcome Evidence
Request a surgical outcomes comparison for the exact operation and cancer type, using the same time period and definitions. A surgeon’s total operation count or years in practice cannot substitute for procedure-specific evidence.
| Measure | What to request | Why it matters |
|---|---|---|
| Annual procedure volume | Number of your planned operation performed each year | Shows current experience with that procedure |
| Major complication rate, readmission rate after surgery, reoperation rate, and operative mortality | Percentages, follow-up period, and whether emergency cases are included | Reveals serious harm and recovery problems |
| Positive margins and negative margins | Pathology results for comparable cancers and stages | Shows whether tumors were removed with an adequate cancer margin |
| Length of stay | Typical and range, separated by uncomplicated and complicated cases | Helps you judge recovery and hospital burden |
| Conversion from minimally invasive to open surgery | Rate and the reasons for conversion | Shows how often the planned approach changes and why |
Compare risk-adjusted results when available; age, cancer stage, prior operations, and other illnesses can change outcomes. A high-volume hospital is associated with lower operative mortality for some complex cancer procedures, but volume does not guarantee your result.
Check whether the hospital has a 24-hour intensive care unit and interventional radiology for bleeding, drainage, or other urgent problems. Also weigh travel, accommodation, and family support: a distant center can offer strong capabilities but make daily recovery and rapid review harder.
A survival percentage alone is not a fair surgeon comparison unless you know which patients and follow-up period it covers.
Use the First Consultation to Test the Treatment Plan
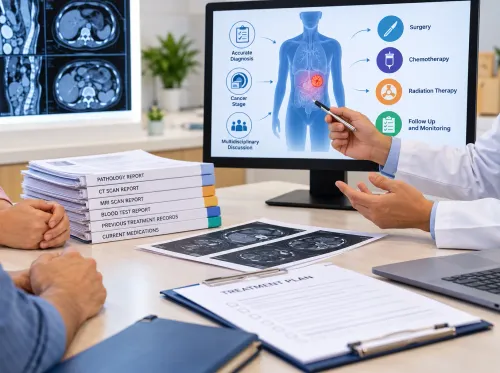
Ask whether the operation’s goal is complete tumour removal with negative margins, appropriate lymph-node assessment, and preservation of function when safe. Then test whether surgery is the first step or whether chemotherapy, immunotherapy, radiation, or hormone therapy could change its extent or timing.
- Which operation do you recommend, and why is it suitable for my cancer and stage?
- What are the treatment alternatives, including no surgery or treatment before surgery?
- Is minimally invasive surgery appropriate, and what are its specific risks? When would you convert to open surgery?
- Could I need an ostomy or stoma? If so, would it be temporary or permanent?
- Will reconstruction be needed, and who performs it?
- How could this affect fertility or sexual function?
- What is the recovery timeline for hospital stay, pain control, eating, driving, work, and normal activity?
- Which warning signs after discharge require an urgent call or hospital visit?
- What complications, reoperation, readmission, or death risks apply to this operation?
- What will you do if you find more disease, an unresectable tumour, or spread during surgery?
For extensive, irreversible, rare, or function-changing surgery, obtain a second opinion using the pathology slides and tissue blocks, imaging files and reports, laboratory results, and written operative recommendation. A verbal summary is not enough.
Whether you consult Dr.Parag Ingle - Surgical Oncologist or another specialist, ask how unexpected findings would change the plan before signing consent.
Related services
Surgery for cancer We are dedicated to provide advanced and compassionate care. Our skilled and experienced surgical team employs state-of-the-art techniques to remove... View service → |
Oral cancer treatment involves various medical procedures to address cancerous growth in the mouth. View service → |
Choose a Team That Can Manage the Whole Cancer Journey
Ask whether your case will be reviewed at a multidisciplinary tumor board by a medical oncologist, radiation oncologist, radiologist and pathologist, with genetics and supportive-care input when relevant. The board should use your completed imaging and pathology, not merely exist as a marketing label. Ask who explains the final recommendation and what would change it.
Before scheduling surgery, expect an anesthesia assessment covering diabetes and heart-lung disease, anticoagulants, smoking, nutrition, frailty, and your ability to walk and manage daily tasks. A complete plan may include smoking cessation, medication changes, nutritional support, exercise-based prehabilitation, and an enhanced-recovery pathway. If these topics never arise, the preparation process is incomplete.
Judge support after discharge by named people and specific arrangements, not promises. Ask who handles fever, bleeding, wound problems, pain, or poor eating; whether a reconstructive surgeon and dietitian are available; and how follow-up results are communicated.
A palliative-care specialist can help control pain, nausea, fatigue, or other symptoms at any stage, including during treatment aimed at cure. Ask whether family history or tumor features warrant genetic counseling and germline testing before choosing limited or extensive surgery.
| Check | What to ask | Warning sign |
|---|---|---|
| Preparation | Who coordinates anesthesia, optimization, and discharge? | No owner for complications |
| Team review | Which specialists reviewed my case and why? | Generic tumor-board claim |
| Recovery | Who provides reconstruction, nutrition, and symptom support? | No named follow-up contact |
Frequently asked questions
How do I know whether surgery is the right first treatment?
Review the cancer stage, biopsy findings, specialist pathology opinion, CT, MRI, and PET-CT results, then clarify whether treatment aims to cure, control, or relieve symptoms.
Which credentials and experience should I check?
Confirm the surgeon’s specialist training and ask how often they perform your exact operation for your cancer type.
What hospital evidence should I compare?
Compare the hospital’s experience with the procedure, reported outcomes, complication management, intensive care access, and multidisciplinary cancer support.
What should I ask during the first consultation?
Ask about the diagnosis, treatment alternatives, surgical risks, expected recovery, likely results, and what happens if the operation finds more advanced disease.
Why does a whole cancer-care team matter?
Cancer treatment can require coordinated input from surgical, medical, and radiation oncologists, radiologists, pathologists, nurses, rehabilitation specialists, and palliative-care professionals.
Related services
Targeted therapy for cancer Experience cutting-edge cancer treatment with our targeted therapy services. View service → |
Gynaecological cancer treatment Gynaecological cancer treatment We offer comprehensive gynaecological cancer treatment services dedicated to women's health. View service → |
Esophageal cancer treatment Our Esophageal Cancer Treatment services provide comprehensive care for individuals battling esophageal cancer. View service → |
Stomach cancer treatment We provide comprehensive stomach cancer treatment services with a focus on your well-being. View service → |